First question
Independent indication?ACS, significant left main, refractory angina or selected prognostic indication.
Solely to lower surgical risk?Routine intervention for stable non-left-main CAD has not improved principal randomized outcomes.
A
Which evidence applies?
population before extrapolation| Setting | What the evidence supports |
|---|---|
| Elective vascular surgery | CARP: no survival/postoperative-MI benefit. Longer delay. |
| Kidney transplant | ISCHEMIA-CKD/listed subgroup: no routine invasive-strategy benefit for stable moderate/severe ischemia. Immediate transplant evidence limited. |
| Liver transplant | Observational comparisons. Joint coronary-risk, treatment-feasibility and transplant-timing decision. |
B
Count the full pathway
benefit must survive the delayPlaying
- Selection trap Post-transplant survivors cannot establish benefit for everyone evaluated.
- Recommendation Treatment indication, candidacy impact and readiness reassessment owner.
Stable CAD before elective vascular surgery: CARP found no routine revascularization benefit.
A
Trial at a glance
defined, selected populationWho / treatment
- Enrollment 510/5,859 screened (9%), 98% men. Stable CAD, elective AAA/lower-extremity vascular surgery.
- Intervention 59% PCI, 41% CABG among revascularized. No randomized CABG–PCI comparison. Procedure choice was not the randomized question.
Excluded / limits
- Exclusions Left-main ≥50%, EF <20%, severe AS, urgent/emergency surgery.
- Applicability Earlier stent/medical era. Not transplant, ACS or urgent limb salvage. Confidence intervals retain uncertainty.
B
Results
revascularization vs no revascularization| Endpoint | Revascularization versus no revascularization |
|---|---|
| Mortality at median 2.7 years | 22% versus 23%, relative risk 0.98, 95% CI 0.70-1.37, P=0.92 |
| MI within 30 days after vascular surgery | 12% versus 14%, P=0.37 |
| Median randomization-to-vascular-surgery interval | 54 versus 18 days, P<0.001 |
C
Apply the 2024 AHA/ACC guideline
indication beyond the operation- ACS Treat, then defer elective surgery.
- Significant left main ≥50% Revascularization reasonable when hemodynamically significant.
- Stable non-left-main Do not intervene routinely solely to lower perioperative events.
- Before another test Specify how anatomy would reveal an independent indication or change the operation.
ISCHEMIA-CKD: medical therapy is the foundation for comparable stable advanced-CKD disease.
A
Strategy trial
777 patientsEntry + comparison
- Entry eGFR <30 mL/min/1.73 m² or dialysis, stable moderate/severe ischemia.
- Comparison Initial invasive strategy + medical care versus medical care with angiography for clinical failure. Rescue intervention allowed. Conservative care was active medical treatment.
Important exclusions
- Disease Refractory angina, recent ACS, EF <35%, NYHA III/IV HF/recent HF admission, known or strongly suspected significant unprotected left-main disease.
- Imaging / surgery Routine CCTA to exclude unknown left main discouraged for kidney risk. Planned major surgery requiring DAPT interruption excluded.
B
Outcomes and treatment exposure
invasive vs conservative| Outcome or treatment exposure | Invasive versus conservative strategy |
|---|---|
| Estimated 3-year death or nonfatal MI | 36.4% versus 36.7%, adjusted HR 1.01, 95% CI 0.79-1.29 |
| Stroke | HR 3.76, 95% CI 1.52-9.32 |
| Death or initiation of dialysis | HR 1.48, 95% CI 1.04-2.11. This safety analysis concerned participants not receiving dialysis at baseline |
| Cumulative revascularization at 3 years | 50.2% versus 19.6% |
C
What changes practice?
no automatic invasive mandate- Ischemic burden alone No demonstrated routine invasive-strategy benefit.
- Still assess anatomy If it creates an independent indication or changes candidacy. Weigh renal injury, bleeding and delay.
- Do not extrapolate Not CABG versus PCI, immediate transplant surgery, ACS, refractory symptoms, severe LV dysfunction or significant left-main treatment.
Modern stable-CKD strategy evidence outweighs a small historical transplant trial for comparable patients.
A
ISCHEMIA-CKD listed subgroup
post hoc · 194 candidatesDeath/nonfatal MI
27/94 vs 30/100
Invasive vs conservative.
Adjusted effect
HR 0.91
95% CI 0.54–1.54.
Transplanted
51
Treatment-by-list-status interaction P=0.68.
- Limit Small post hoc subgroup, wide interval and substantial crossover. Absence of significance does not establish equivalence. Immediate transplant-operation benefit remains imprecise.
B
Manske 1992
historical comparatorPopulation + result
- Population 26 insulin-dependent diabetic patients with atypical or no chest pain, chronic renal failure, substantial CAD during transplant assessment.
- Unstable angina, MI or cardiac death 10/13 medical vs 2/13 revascularization, median 8.4 months.
Why not a modern rule?
- Medical care Calcium-channel blocker + aspirin, not contemporary prevention.
- Inference Small sample, limited precision/generalizability. No predicted transplant benefit assignable from either trial.
C
Decision before PCI
indication + offer access- Assess Symptoms, LV function, anatomy, feasible medical care, independent indication, procedural risk and time away from readiness.
- Donor pathway Living donation allows scheduling. Deceased-donor offers require an explicit antiplatelet/readiness plan.
No randomized liver-transplant trial establishes benefit from routine prophylactic PCI.
A
Recipient cohort versus evaluation cohort
denominator changes the questionUmadat 2025: post-LT outcomes
- Population 111 asymptomatic recipients with significant angiographic CAD. 66 PCI, 45 medical. CABG excluded.
- MACE 52% vs 60% at median 32 months, P=0.40.
- Unadjusted HR 1.16, 95% CI 0.68–1.96.
- Composite Death, MI, stroke/TIA, new systolic dysfunction or post-LT coronary intervention.
- Limit Small single-center cohort selected by reaching transplantation. No demonstrated lower MACE, no equivalence conclusion.
Ginard 2025: evaluation harms
- Population 912 evaluated → 202 angiography → 18 PCI.
- Complications 8/202 overall, 4/18 after PCI.
- Death One acute-on-chronic liver-failure death after DAPT-related bleeding.
- Limit Captures pretransplant harm. Small PCI sample, disease-based treatment selection.
- One-month DAPT Used in many PCI patients. Does not establish universal transplant timing.
B
AASLD/AST 2026 decision
individual benefit and feasibility- Current guidance Significant asymptomatic CAD: multidisciplinary revascularization assessment before/around LT. Replaces older broad consideration for all significant CAD.
- Balance Lesion significance, hepatic reserve, portal bleeding, kidneys, DAPT tolerance, delayed listing and declined organs.
- Endpoint caution Umadat MACE is broader than CARP/ISCHEMIA-CKD endpoints.
Selected recipient survival demonstrates feasibility, not a causal revascularization benefit.
A
Wray 2025
historical cohort, long follow-upCohort
604 recipients
Pre-LT angiography, 7 centers, transplantation 1998–2010.
CAD / follow-up
145 obstructive CAD
Mean follow-up 7.3 years.
| Comparison with recipients without obstructive CAD | Adjusted mortality association |
|---|---|
| Any obstructive CAD | HR 1.39, 95% CI 1.06-1.82 |
| Severe CAD, >70% stenosis | HR 1.63, 95% CI 1.19-2.22 |
| Pretransplant revascularization | HR 1.62, 95% CI 1.18-2.23 |
B
Read the comparison correctly
against recipients without obstructive CADWhat HR 1.62 cannot show
- Causal harm Revascularized patients differ from recipients without CAD.
- Risk eliminated Successful treatment does not remove long-term coronary risk.
Cohort checks
- Start point Evaluation, listing or transplantation?
- Comparator Similar anatomy/symptoms? Treatment selected for worse disease?
- Missing interval Deaths, bleeding, delisting and missed organs before LT?
- Era Current stents, medical care and selection?
C
Residual risk
complete the whole assessment- Beyond coronaries HF, RV/vascular disease, frailty and transplant hemodynamic stress.
- Outcome horizon Post-LT survival is one part of evaluation-to-transplant survival.
A
Contemporary selected cirrhosis cohort
Jenkins · cardiac surgery with cardiopulmonary bypass30-day mortality
4.1%
220 patients, median MELD 10.
90-day mortality
12.6%
Operated 2014–2022. Recovery deaths matter.
- By class at 30 days A: 2.8% (n=143). B: 6.8% (n=73). Only 4 class C patients.
- Selection Confirmed cirrhosis. Prior/concomitant LT and off-pump operations excluded. Declined patients absent.
B
Historical severity gradient
Jacob · 19 studies · 638 patients| Child-Pugh class | Deaths / patients | Pooled mortality, 95% CI |
|---|---|---|
| A | 38/420 | 9.0% (6.6-12.2%) |
| B | 72/193 | 37.3% (30.8-44.3%) |
| C | 13/25 | 52.0% (33.5-70.0%) |
- Endpoint Pooled short-term mortality <30 days, variable component follow-up. Mixed CABG/valve studies through early 2014.
- Limit Heterogeneous historical data, class C n=25. Not a contemporary risk calculator or an individual CABG estimate. Keep the operation and follow-up horizon attached to each rate.
C
Death and decompensation
Suman · 44 cardiac-surgery patients with CPB · 1992–2002| Child-Pugh class, n | Mortality | Hepatic decompensation |
|---|---|---|
| A, 31 | 1/31 (3.2%) | 3/31 (9.7%) |
| B, 12 | 5/12 (41.7%) | 8/12 (66.7%) |
| C, 1 | 1/1 | 1/1 |
- By 3 months 7/44 deaths, 12/44 hepatic decompensations. These are not 30-day rates.
- Class C One patient cannot estimate class-specific risk. Contemporary selected outcomes do not erase advanced-disease risk.
Mortality alone misses hepatic decompensation, renal injury, ventilation and lost transplant opportunity.
A
Broader liver disease, not cirrhosis alone
Pétursson · 285 patients · 2010–2020| Group, n | Death by 30 days / in hospital | ≥1 complication |
|---|---|---|
| Child-Pugh A, 219 | 5.9% | 37.9% |
| Early B, MELD <12.7, 34 | 5.9% | 38.2% |
| Advanced B, MELD ≥12.7, 32 | 18.8% | 59.4% |
- Advanced B Renal failure 21.9%, prolonged ventilation 46.9%.
- Selection No class C. Early B younger, frequent endocarditis/tricuspid surgery. Conventional MELD 12.7 derived within this dataset.
- Inference No universal “safe MELD” for CABG.
B
Other outcome estimates
keep endpoints distinct2025 cirrhosis meta-analysis
- Inpatient mortality 11% (95% CI 9–14%).
- Renal failure 30% (21–39%), not an estimate of new dialysis. Check component definitions.
Individual assessment
- Hepatic Child-Pugh points, dated MELD/version, ascites/encephalopathy, portal bleeding.
- Operative Kidney reserve, nutrition/frailty, urgency and complexity. Cardiac-surgery/hepatology adjudication.
- Versions MELD, MELD-Na and MELD 3.0 cutoffs are not interchangeable. Record the score version used by the study and calculator.
C
Calibration in 220 operated patients
Jenkins: mean prediction vs observation| Model or observed outcome | 30-day mortality | 90-day mortality |
|---|---|---|
| Mayo model, mean predicted | 20.9% | 29.6% |
| VOCAL-Penn, mean predicted | 9.0% | 14.0% |
| Observed | 4.1% | 12.6% |
- Limits Nine 30-day deaths. Mean estimates are not individual corrections or evidence of safety for patients declined surgery.
- Report Calculator, endpoint and limitations.
CABG decision
IndicationCoronary benefit must be established.
FeasibilityHepatic reserve and transplant rescue require separate assessment.
A
CABG-specific absolute risk
Siraw · US inpatient data · 2016–2020Cirrhosis
8.6%
In-hospital mortality.
Noncirrhotic liver disease
5.9%
In-hospital mortality.
No chronic liver disease
2.8%
In-hospital mortality.
- Population 7,945 chronic-liver-disease patients matched to 7,945 without. Cirrhosis n=6,687.
- Adjusted association Mortality OR 4.21 (95% CI 3.61–4.94). No granular Child-Pugh/MELD severity.
B
Avoiding bypass ≠ established safety
Gopaldas · 1998–2009Observed association
- Population 6,448 cirrhotic patients among about 3 million CABG admissions.
- On-pump Excess mortality/morbidity across severity categories.
- Off-pump Association concentrated in severe disease, defined administratively. No causal off-pump benefit or advanced-cirrhosis safety claim. Operative selection can explain part of the association.
Clinical boundary
- Technical Suitability and completeness still matter.
- AHA 2022 Isolated CABG described as contraindicated at MELD >13 or Child-Pugh B/C.
- Adjudication Experienced team, especially with decompensation. New mixed-operation cohorts do not validate CABG across class B.
C
Simultaneous cardiac surgery + LT
selected-center feasibility- 2026 report 46 selected patients, CABG/valve mix. Actuarial survival 74.2% at 1 year, 50% at 5 years.
- Limits Single center, nonrandomized, not CABG-specific. No staged-care superiority or broadly validated internal score.
- Plan Medical care, PCI, staged CABG, selected combined surgery or prohibitive risk. Transplant impact and reassessment owner.
A
Choose treatment after establishing an indication
coronary guideline conditionsCABG when surgically suitable
- Left main Recommended for significant disease.
- LV dysfunction Recommended: multivessel CAD, severe LV dysfunction and amenable anatomy.
- Diabetes Preferred: multivessel disease involving LAD, in a suitable surgical candidate.
PCI consideration
- Left main Selected anatomy permitting equivalent revascularization.
- Surgery unsuitable PCI remains an option when revascularization is indicated.
- Heart Team Symptoms, anatomy, LV function, completeness, harm, DAPT, preference and life expectancy.
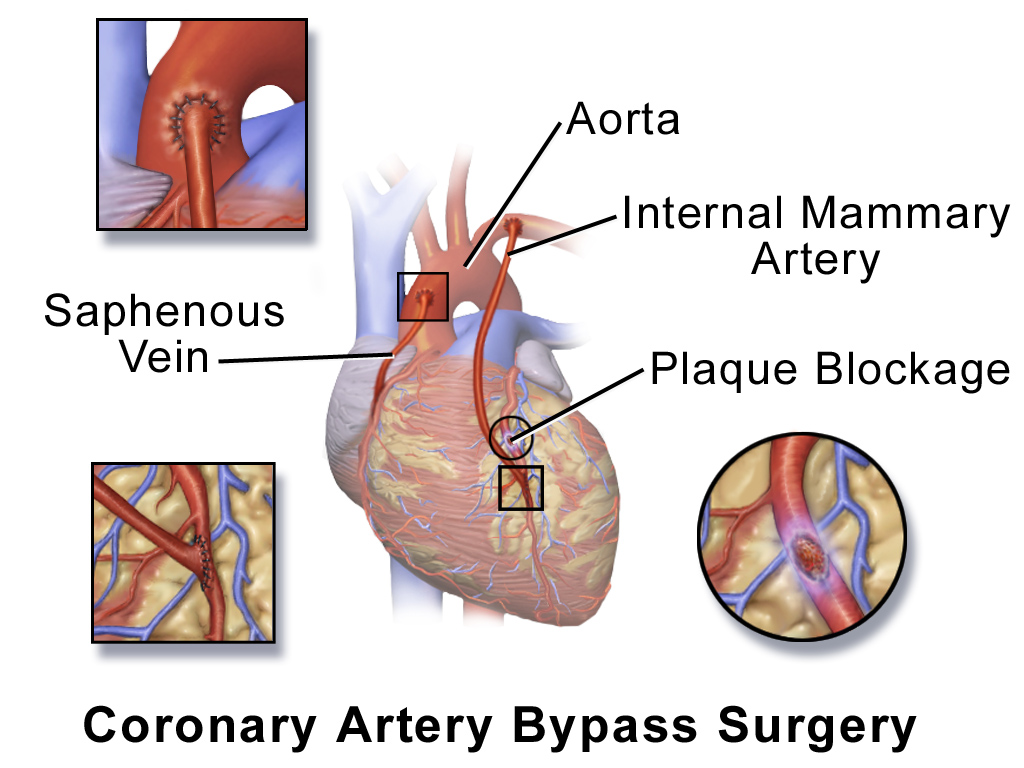
Blausen 0151 CABG 02.png by BruceBlaus / Blausen Medical Communications. Source · CC BY 3.0. Unmodified.

B
Evidence: match population and comparator
no cross-trial CABG–PCI inference| Trial / population | Outcome | Clinical lesson |
|---|---|---|
| FREEDOM · 1,900 Diabetes, multivessel CAD | 5-year death/MI/stroke: 26.6% PCI vs 18.7% CABG. Stroke: 2.4% vs 5.2%. | CABG benefit, stroke tradeoff. Earlier DES era. |
| STICHES · 1,212 EF ≤35%, CABG-amenable CAD | Median 9.8 years: death 58.9% CABG vs 66.1% medical. HR 0.84 (95% CI 0.73–0.97). | Selected ischemic CM: long-term CABG benefit, with recovery/time-to-benefit costs. |
| REVIVED-BCIS2 · 700 EF ≤35%, extensive CAD, viability | Median 41 months: death/HF admission 37.2% PCI vs 38.0% medical. HR 0.99 (95% CI 0.78–1.27). | No demonstrated endpoint benefit. Viability alone does not establish prognostic PCI benefit. |
C
Transplant boundary
benefit must fit the patient- Limits Different questions and populations. No immediate liver/kidney-transplant protection estimate or randomized STICHES–REVIVED comparison.
Dialysis CABG–PCI evidence is observational, with conflicting survival signals.
A
Compare early harm and later outcomes
treatment selection remainsUSRDS · Chang 2012
- Population 21,981 dialysis patients, multivessel CABG versus PCI, 1997–2009.
- Death CABG HR 0.87 (95% CI 0.84–0.90).
- Death/MI HR 0.88 (95% CI 0.86–0.91).
- Limit Administrative data, older PCI era, selection/residual confounding.
Taiwan · Pan 2024
- Population 1,840 propensity-matched dialysis patients, 2009–2015, CABG versus DES PCI.
- In-hospital death 12.5% vs 3.3%.
- Overall mortality HR 1.19 (95% CI 1.05–1.35), favoring PCI, median 2.8 years.
- Tradeoff More repeat revascularization, ACS and rehospitalization after PCI. Observational population/practice differences.
B
What these cohorts cannot establish
no prophylactic-transplant comparison- Confounding Anatomy, frailty, urgency and surgical selection persist despite adjustment. Transplant candidates may have different competing risk.
- Question Neither tested routine intervention versus medical care before transplantation.
C
Individual comparison
when revascularization is indicated- Coronary Anatomy/completeness, diabetes, LV function, conduits, CABG recovery, PCI complexity and DAPT.
- Transplant Nephrology constraints, expected survival with/without transplant and time away from readiness.
- Counsel No randomized dialysis-specific CABG superiority established by these cohorts. Shorter PCI recovery alone does not settle treatment.
Two decisions
DAPT durationAbbreviated therapy retains a defined antithrombotic regimen.
Permission to operateDepends on interruption, bleeding, thrombosis and urgency.
A
2024 AHA/ACC surgical timing
planned noncardiac surgery| PCI context | Timing anchor |
|---|---|
| Balloon angioplasty without stenting | Delay elective surgery ≥14 days |
| DES for ACS | Ideally delay elective surgery ≥12 months |
| DES for chronic coronary disease | A delay ≥6 months is reasonable for elective surgery |
| Time-sensitive surgery after DES | May be considered ≥3 months when the harm of delay exceeds cardiac risk |
| BMS or DES within 30 days | Elective surgery requiring antiplatelet interruption is potentially harmful |
- DES rows Assume interruption of ≥1 antiplatelet agent.
- Early time-sensitive surgery Continue DAPT within 30 days of BMS or <3 months of DES unless bleeding outweighs thrombosis protection.
- Aspirin Continue low dose after PCI when feasible.
B
MASTER DAPT
4,579 high-bleeding-risk patientsWhat was tested
- Entry Event-free first month after a specific contemporary DES.
- Net events Per-protocol death/MI/stroke/major bleeding: 7.5% abbreviated vs 7.7% standard, noninferior.
- Bleeding Intention-to-treat major/clinically relevant nonmajor bleeding: 6.5% vs 9.4%.
What was not tested
- Transplant Routine liver/kidney transplantation at one month with all antiplatelets stopped. Short DAPT is not zero antiplatelet therapy.
- Stent protection Heparin does not replace antiplatelet protection.
C
Organ-offer plan before PCI
interventional + transplant + anesthesia- Decide Accept on current therapy, allow interruption or wait? Include harm of delay and individual urgency.
- Handoff Actual last doses, restart ownership and anesthesia restrictions.
No randomized trial establishes a universal CABG-to-transplant waiting interval.
A
Recovery determines readiness
clinical domains, not a validated scoreCardiac + systemic
- Cardiac Indication/grafts, perioperative MI/stroke, rhythm, residual ischemia, ventricular function/congestion.
- Systemic Lung/kidney recovery, anemia, infection, wound/sternum, activity, nutrition and rehabilitation.
Treatment + timing
- Antithrombotics Aspirin, P2Y12 indication, OAC and anesthesia/bleeding plan. CABG does not erase constraints, especially after ACS.
- Cost of delay Malignancy, limb threat, organ failure and operative urgency.
B
Mallick timing association
US readmissions data · 2016–2020Source population
1,335,175
Elective cardiac operations. CABG, valve and combined.
Subsequent surgery
20,253
Patients undergoing subsequent noncardiac surgery.
- Around 100 days Modeled inflection. Later surgery: major adverse events adjusted OR 0.69 (95% CI 0.62–0.76).
- In-hospital death Adjusted OR 0.66 (95% CI 0.46–0.96).
- Limits Administrative/observational, not CABG-only or transplant-specific. Composite includes cardiac, neurologic, respiratory, renal and other serious complications.
- Inference No proof every patient benefits from waiting 100 days. An observational inflection is not a mandatory waiting period.
C
Conclude with conditions
operation or organ offer- Planned surgery Earliest reasonable reassessment, residual disease and recovery.
- Transplant Offer availability and remaining activation/acceptance conditions.
- Cardiac operation Valve/CABG optimization, ICU handoff and recovery.
A
Resolve the decision
clinical state → indication → feasibilityStabilityACS, unstable symptoms, HF/arrhythmia first. Actual activity and limitations.
Coronary significanceDated anatomy/physiology, left main, LV function and prior treatment.
Independent indicationSymptom or prognostic benefit, with expected time to benefit.
FeasibilityMedical care, PCI, CABG or selected combined options. Renal/hepatic reserve and patient priorities.
B
Consultation fields
fill with verified evidenceTreatment decision
- Context [ ] Operation/organ, stability, dated anatomy/ischemia and LV function.
- Treatment [ ] Independent indication or none solely to lower operative risk. Feasible medical care, limitations and chosen option.
- Benefit/harm [ ] Applicable population/limits, time to benefit, kidneys/liver, bleeding, recovery/DAPT and transplant/surgical delay.
Liver + operative plan
- Cirrhosis [ ] Child-Pugh points, dated MELD/version, decompensation, 30-/90-day mortality and hepatic complications, with source/limits.
- Readiness [ ] Proceed / optimize / team pending / prohibitive. Conditions, reassessment owner/date and the evidence needed to change the decision.
- Offer/operation [ ] Dates, antiplatelets, interruption/restart and harm of waiting.
C
Complete the wider assessment
linked workups- Companions Perioperative assessment and organ-specific transplant workups.