Name the vascular bed and the clinical problem. This guide covers lower-extremity PAD, carotid and subclavian disease, renal artery stenosis, fibromuscular dysplasia, and venous disease. Start with the threatened organ and the time course. Start with plaque, FMD or vasculitis to distinguish arterial causes. For fibromuscular dysplasia (FMD), see diagnosis, treatment, follow-up and counseling, and the imaging atlas.
1
Name the clinical subset first
four phenotypes · four pathwaysA · asymptomaticObjective PADNo reported exertional leg symptoms. Functional impairment may still be present. Treat systemic risk—do not revascularize solely to prevent progression.
B · chronic symptomaticClaudication / atypical symptomsExertional leg discomfort or walking limitation without rest pain or tissue loss. Confirm physiology, then exercise + GDMT.
C · limb threatenedCLTIIschemic rest pain, nonhealing wound/ulcer, or gangrene lasting >2 weeks with objective hypoperfusion. Limb-preservation pathway.
D · emergencyAcute limb ischemiaSudden hypoperfusion ≤2 weeks: pain, pallor, pulselessness, coolness, paresthesia, or paralysis. Heparin + vascular evaluation now.
2
Pattern-match the symptom
arterial vs common mimics| Pattern | Typical history / exam | Bedside read |
|---|---|---|
| Arterial claudication | Reproducible exertional calf, thigh, or buttock fatigue/ache. Relief within minutes of rest. Reduced pulses/bruits | Calf → femoropopliteal. Thigh/buttock → aortoiliac. Atypical exertional symptoms are common—do not require the textbook story. |
| CLTI rest pain | Forefoot pain at rest, worse with elevation/overnight. Relief with dependency. Ulcer/gangrene. Cool, shiny, hairless foot | Urgent vascular + wound/podiatry assessment. ABI can be falsely reassuring in diabetes/CKD—add toe or tissue perfusion. |
| Venous | Heaviness/aching, edema, varicosities, stasis change. Often improves with elevation | Pulses usually present. Consider venous reflux/DVT pathway rather than labeling all leg symptoms “PVD.” |
| Neurogenic / MSK | Variable distance. Posture/back/joint related. Relief with sitting or flexion rather than standing alone | Normal vascular physiology redirects the differential. Coexistence with PAD is common. |
3
Resting ABI — calculate and interpret
higher ankle ÷ higher brachial
Formula · each leg
ABI = max(DP, PT) / max(right arm, left arm)
Measure after supine rest with Doppler waveforms and/or pulse-volume recordings when available. A marked inter-arm pressure difference is itself a vascular clue.
≤0.90Abnormal · establishes PAD in the appropriate clinical setting
0.91–0.99Borderline · exercise ABI if exertional symptoms
1.00–1.40Normal · exercise ABI if symptoms remain suspicious
>1.40Noncompressible · obtain toe-brachial index (TBI). TBI ≤0.70 is abnormal
4
Physiology → anatomy only when needed
choose the next test for the decisionSymptoms + normal/borderline ABIExercise treadmill ABIConfirms exertional pressure drop and objectively measures walking limitation.
ABI >1.40 · diabetes · CKDToe pressure / TBIDigital arteries are less often noncompressible. Add waveforms.
CLTI / woundLocal perfusionToe pressure/TBI, transcutaneous O₂, or skin-perfusion pressure estimates healing potential.
Revascularization consideredDuplex · CTA · MRADefine lesion level and plan treatment. Invasive angiography when proceeding or noninvasive imaging is inadequate.
Document the limb, not just “pulses.” Femoral/popliteal/DP/PT pulse grade · Doppler arterial and venous signals · temperature/color · capillary refill · sensation/motor function · every wound’s location, size, depth, drainage, infection, and offloading status.
PAD is systemic atherosclerotic disease. Every visit must reduce both MACE (CV death/MI/stroke) and MALE (acute limb ischemia/major amputation/revascularization). For claudication, structured exercise is first-line therapy, not an afterthought.
1
Antithrombotic selector
match ischemic benefit to bleeding risk| Clinical setting | Guideline option | Guardrail |
|---|---|---|
| Symptomatic PAD | Single antiplatelet: clopidogrel 75 mg daily or aspirin 75–325 mg daily | Generally use one agent. Routine chronic DAPT without recent revascularization has uncertain benefit. With clopidogrel, avoid omeprazole/esomeprazole. |
| Symptomatic PAD · low bleed risk | Dual-pathway inhibition: rivaroxaban 2.5 mg BID + aspirin 75–100 mg daily | More bleeding. Do not use with active pathologic bleeding. Avoid Child-Pugh B/C or hepatic coagulopathy, strong combined P-gp/CYP3A interactions, or another anticoagulant. Severe renal-failure evidence is limited. |
| After endovascular revascularization | Choose a deliberate strategy: rivaroxaban 2.5 mg BID + low-dose aspirin is recommended. DAPT (P2Y12 + aspirin) is reasonable for 1–6 months. | These are not automatically stacked. Start rivaroxaban after hemostasis. Device, competing anticoagulation, and bleeding risk shape the discharge plan. |
| After surgical revascularization | Antiplatelet therapy. Rivaroxaban 2.5 mg BID + aspirin. After a prosthetic graft, DAPT ≥1 month may be reasonable. | Autogenous-vein and prosthetic conduits are not interchangeable. Follow the vascular team’s discharge plan. |
| Full-dose OAC indication | Continue therapeutic anticoagulation for AF/VTE/mechanical indication. Adding single antiplatelet may be reasonable after revascularization if bleed risk is not high. | Do not use full-intensity anticoagulation solely to prevent PAD MACE/MALE. Avoid unplanned triple therapy. |
2
The non-negotiable prevention bundle
prescribe · verify · intensifyLipidsHigh-intensity statinAim ≥50% LDL-C reduction and LDL-C <55 mg/dL for very-high-risk ASCVD or <70 mg/dL for other clinical ASCVD. Add nonstatin therapy as needed. Very high risk means multiple major ASCVD events, or one plus multiple high-risk conditions.
Blood pressureGoal <130/80Treat hypertension. ACE inhibitor or ARB is useful for MACE reduction when clinically appropriate.
DiabetesCardioprotective agentsUse GLP-1 receptor agonist and/or SGLT2 inhibitor when appropriate. Optimize glucose without ignoring feet, kidneys, or nutrition.
TobaccoTreat every visitAsk, advise, assist. Combine counseling with varenicline, bupropion, and/or nicotine replacement when appropriate. Avoid secondhand smoke.
3
Claudication — make walking a prescription
exercise before elective revascularizationSupervised / structured walking
- Frequency 3 sessions/week for ≥12 weeks. Supervised exercise therapy is preferred when accessible.
- Session warm up → intermittent walking → cool down. Build toward 30–45+ min of exercise excluding rests.
- Intervals walk until moderate-to-severe claudication, rest until it resolves, repeat. Increase duration/intensity progressively.
- Cannot walk? structured cycling, arm ergometry, or other nonwalking exercise can help.
Cilostazol — symptom drug, not event prevention
Cilostazolclaudication only
100 mg BID, ≥30 min before or 2 h after meals. stop if no improvement after 3 months.
Never in HFboxed warning
Contraindicated in heart failure of any severity. Use caution with ischemic heart disease or tachyarrhythmia. Avoid with active bleeding.
Interactionsdose reduce
50 mg BID with strong or moderate CYP3A4 inhibitors, or with CYP2C19 inhibitors. Verify the current label and medication list.
Do not substitute
Pentoxifylline and chelation are not recommended for claudication.
4
When claudication reaches revascularization
function + goals + anatomyConfirm Objective PAD + symptom/lesion concordance. Document baseline walking limitation and patient-defined goals.
Deliver GDMT Antithrombotic plan, lipid/BP/diabetes/tobacco care, foot care, and an adequate structured-exercise trial.
Adequate response Continue GDMT + exercise. Do not revascularize when function and quality of life are acceptable.
Still function-limiting Shared decision + anatomic imaging. Endovascular, surgical, or hybrid therapy is reasonable to improve walking and quality of life.
Foot protection: patient checks daily. Clinician inspects at every visit and performs a comprehensive foot evaluation at least annually. Wash and dry, moisturize (not between toes), never walk barefoot, and use therapeutic footwear when deformity, callus, neuropathy, or prior ulcer/amputation raises risk.
Chronic limb-threatening ischemia (CLTI) requires prompt limb-preservation care. Ischemic rest pain, a nonhealing ulcer/wound, or gangrene with objective hypoperfusion requires rapid multispecialty evaluation. Revascularization is recommended when feasible to heal tissue, relieve pain, minimize loss, and preserve a functional limb.
1
First encounter — define threat and control infection
same-day decisionsEscalate nowSepsis · wet gangrene · deep infectionCultures when appropriate, IV antibiotics, urgent drainage/debridement, and vascular input. Coordinate source control with perfusion restoration—sequence is patient-specific.
Stage the limbWIfIWound extent + Ischemia + foot Infection estimates amputation risk and potential revascularization benefit. Photograph and measure consistently.
Stage the patientRisk · function · goalsFrailty, life expectancy, ambulatory potential, heart/kidney disease, conduit, anatomy, prior procedures, cognition, and the patient’s acceptable outcome.
2
Prove and localize perfusion
ABI alone can miss severe disease| Test | Use in CLTI | Interpretation / trap |
|---|---|---|
| ABI + waveforms | Global starting point. Segmental pressures/PVR help localize level | Diabetes, CKD, and medial calcification can produce falsely high/noncompressible ABI. A normal-looking ABI does not overrule an ischemic wound. |
| Toe pressure / TBI | Preferred when ankle arteries are noncompressible. Better reflects distal perfusion | TBI ≤0.70 supports PAD. toe pressure <30 mmHg indicates severe ischemia and poor healing potential. |
| TcPO₂ / SPP | Local tissue-perfusion and healing assessment around a wound or amputation level | Interpret with edema, infection, temperature, probe site, and technical quality. Trend after revascularization. |
| Duplex · CTA · MRA · angiography | Map inflow, femoropopliteal, tibial, pedal, and wound-directed targets | Choose the modality around kidney function, calcification, contrast, hardware, urgency, and whether intervention will occur in the same setting. |
3
Limb-preservation bundle
revascularization is necessary, not sufficientPerfusionRestore flowAim for in-line blood flow or maximal perfusion to the wound bed. Rest pain with multilevel disease often starts with inflow correction.
InfectionTreat promptlyAntibiotics + drainage/debridement when indicated. Evaluate osteomyelitis. Do not wait for a perfect vascular workup in a septic foot.
PressureOffloadIndividualized offloading is essential, especially for a diabetic plantar ulcer. Protect the heel and contralateral foot.
HostOptimize healingGlycemia, nutrition/protein, edema, anemia, renal care, tobacco cessation, mobility, pain, and social barriers.
4
Choose a revascularization strategy
patient · limb · anatomy · conduitEndovascular may favor
- High surgical risk, limited conduit, less complex anatomy, or need for a lower-physiologic-stress approach.
- Angioplasty ± stent/atherectomy according to vessel, lesion, calcium, prior repair, and operator strategy.
- Plan for durability and surveillance. Repeated procedures may be part of the tradeoff.
Bypass may favor
- Acceptable operative risk, suitable target, complex/diffuse disease, and a good single-segment great saphenous vein.
- In BEST-CLI cohort 1, vein bypass reduced major adverse limb events or death versus an endovascular-first strategy. This does not generalize to patients without suitable vein.
- Preserve potential targets and conduit when staging or sequencing procedures.
5
Close the loop after revascularization
healing trajectory is the endpointHemostasisLock the antithrombotic planAgent(s), dose, duration, indication, stop date, interactions, and who owns changes.
PerfusionRecord a new baselinePulses/Doppler, ABI/TBI/toe or tissue perfusion as appropriate, and the exact treated segments.
WoundMeasure seriallySize/depth/tissue/infection/offloading. If healing stalls, reassess perfusion, infection, pressure, nutrition, and adherence.
SurveillanceFollow every repairPeriodic clinical review for all. After endovascular repair or autogenous-vein bypass, ABI + duplex at 1–3, 6, and 12 months, then annually is reasonable. Symptoms or wound decline prompt urgent testing. Prosthetic-graft surveillance evidence is uncertain.
Primary amputation is not “failure” when the limb is unsalvageable or reconstruction cannot produce a functional outcome. Decide level and timing through shared, multispecialty assessment. Optimize perfusion to the healing level and plan rehabilitation, prosthetics, and contralateral-foot protection.
ALI
Call nowVascular surgery / endovascular team. Transfer if rapid limb assessment and treatment are unavailable.
AnticoagulateTherapeutic IV UFH on diagnosis unless contraindicated. Use a direct thrombin inhibitor for HIT.
ClassifyMotor + sensory exam and continuous-wave arterial/venous Doppler determine viability.
Do not delayAn immediately threatened limb needs urgent revascularization, not a slow imaging sequence.
1
Recognize the six Ps
neurologic loss = advanced ischemiaPainsudden, severe or escalating
Pallormottling / color change
Pulselesscompare both limbs + Doppler
Poikilothermiacool limb
Paresthesiasensory loss = threatened
Paralysismotor loss = immediately threatened/irreversible
2
Rutherford viability drives the clock
sensory · motor · Doppler| Category | Neurologic findings | Doppler signals | Action |
|---|---|---|---|
| I · viable | No sensory loss · no weakness | Arterial audible · venous audible | Urgent evaluation. Imaging can define anatomy while anticoagulated. |
| IIa · marginally threatened | Minimal sensory loss (toes) · no weakness | Arterial often inaudible · venous audible | Prompt revascularization. Catheter-based options often feasible. |
| IIb · immediately threatened | Sensory loss beyond toes · mild/moderate weakness | Arterial inaudible · venous audible | Immediate revascularization. Do not delay for nonessential testing. |
| III · irreversible | Profound anesthesia · paralysis/rigor | Arterial and venous inaudible | Do not revascularize a nonviable limb. Individualize urgent amputation versus comfort-focused management. |
3
First 15 minutes
parallel work, not a checklist queueStabilizeIV · monitor · analgesia · NPOAssess shock/other vascular beds. Protect the limb from pressure/trauma. Avoid compression.
HeparinTherapeutic IV UFHGive unless active bleeding/high bleeding risk, aortic dissection, or major vascular trauma changes the balance.
ExamineMark + timestampPulses and Doppler signals, capillary refill, temperature/color boundary, sensory map, motor power—repeat serially.
PrepareCBC · CMP/K · CK · lactate · coags · typeECG and targeted embolic history. Do not let labs delay limb-saving therapy.
4
Revascularization — choose the fastest durable option
cause + anatomy + viability + resourcesCatheter-basedThrombolysis / thrombectomyCatheter-directed thrombolysis, aspiration/mechanical thrombectomy, angioplasty/stenting, or combinations. Suited to selected viable or threatened limbs when bleeding risk and time allow.
Open / hybridEmbolectomy · thrombectomy · bypassOften favored for an immediately threatened limb, large embolus, failed endovascular treatment, infected graft, or anatomy requiring direct repair.
EtiologyPrevent recurrenceIn-situ PAD/graft/stent thrombosis, AF/cardiac embolus, aneurysm, dissection, trauma, HIT, hypercoagulability, cancer, or inflammatory disease.
5
After flow returns — reperfusion can kill
ICU-level surveillance when high riskWatch immediately
- Compartment syndrome escalating pain, tense compartments, pain with passive stretch, sensory/motor decline → urgent surgical assessment. Prophylactic/therapeutic fasciotomy may be needed.
- Re-occlusion / embolization repeat pulse, Doppler, motor, and sensory exams. Sudden loss is an emergency.
Track systemic injury
- Rhabdomyolysis CK, K, bicarbonate, creatinine, urine output. Treat hyperkalemia/acidosis and coordinate renal support.
- Bleeding access site, retroperitoneal, intracranial/systemic after lysis. Reconcile UFH, lytic, antiplatelets, and long-term indication.
BOTTOM LINE
ALI is a clinical diagnosis and a time-critical limb emergency. Give therapeutic UFH unless contraindicated, classify viability at the bedside, and revascularize the salvageable threatened limb without avoidable delay.
STROKE
Activate nowNew focal deficit, aphasia, monocular vision loss, or TIA → stroke pathway. Carotid work-up must not delay IV thrombolysis or thrombectomy evaluation.
SymptomaticIpsilateral retinal or hemispheric TIA/stroke within 6 months. A bruit alone is not “symptomatic.”
ImageDuplex first in most stable patients. Confirm intervention-grade disease with CTA/MRA and report stenosis by NASCET.
Treat allAntiplatelet therapy, high-intensity statin, BP/diabetes control, tobacco treatment, exercise, and diet.
1
Symptoms determine urgency
territory before percentage| Presentation | What counts | Next move |
|---|---|---|
| Recent TIA / stroke | Contralateral weakness/numbness, aphasia (dominant hemisphere), dysarthria, or ipsilateral transient monocular blindness | Urgent brain + vascular imaging, neurology/stroke and vascular consultation. |
| Asymptomatic stenosis | No ipsilateral retinal/hemispheric event in the prior 6 months—including an incidental bruit or imaging finding | Intensive medical management. Revascularization is selective, not automatic. |
| Do not screen broadly | General population without neurologic symptoms or major carotid risk factors | No routine duplex. Selective testing only when discovery could change management. |
2
Symptomatic carotid decision
neurologically stable · audited outcomes70–99% NASCETCEA recommendedFor a suitable patient when the center/operator’s 30-day stroke/death risk is <6%. Treat as soon as safely possible after stabilization.
50–69% NASCETConsider CEABenefit depends on age, sex, comorbidity, anatomy, event type, and perioperative risk. Multidisciplinary review is essential.
<50% NASCETNo carotid procedureUse medical management and investigate other stroke mechanisms.
Timing: for a recent stable, nondisabling stroke, revascularization is generally appropriate once neurologically stable after 48 hours and should occur within 14 days. Do not perform emergency CEA for acute ischemic stroke or unstable neurologic status. Large infarct, hemorrhage, major disability, or thrombolysis changes timing. Use the stroke-center vascular team.
3
CEA, CAS, or medical management?
choose the patient, not just the lesionProcedure selection
- CEA usually preferred for standard surgical-risk symptomatic disease, especially age ≥70 and when treating early after symptoms.
- CAS / TCAR may fit high surgical/anatomic risk or selected younger patients when local expertise and outcomes are excellent. Plan required DAPT and bleeding-sensitive procedures.
- Do not chase a velocity alone use an accredited lab’s criteria and confirm anatomy before intervention.
Asymptomatic disease and special lesions
- Asymptomatic ≥70% Begin intensive medical management and discuss selective revascularization. Chapter 13 explains CREST-2, ECST-2, and the limits of procedure comparisons.
- Near-occlusion Confirm distal-vessel collapse on anatomic imaging. A low velocity can conceal severe disease. Recurrent ipsilateral events despite medical therapy require multidisciplinary review, rather than applying the usual stenosis thresholds.
- Free-floating thrombus Urgent neurovascular review and a dedicated antithrombotic plan. Do not treat it as routine fixed plaque stenosis.
BOTTOM LINE
Recent ipsilateral neurologic symptoms create urgency. Confirm the territory and NASCET severity, deliver intensive medical therapy to everyone, and route symptomatic ≥50% disease rapidly to an experienced carotid team.
Steal phenomenon is an imaging finding. Steal syndrome is symptomatic. Proximal subclavian stenosis can reverse ipsilateral vertebral flow to supply the arm. Treat the patient’s arm, brain, coronary, or dialysis-access ischemia—not retrograde flow alone.
1
Recognize the four clinical patterns
measure BP in both armsArmClaudication / ischemiaExertional fatigue, pain, coolness, weak pulse, delayed healing, rest pain, or digital embolization. A persistent inter-arm systolic difference >10–15 mmHg is a clue, not a diagnosis.
BrainSubclavian steal syndromeVertebrobasilar symptoms—vertigo, diplopia, ataxia, dysarthria, syncope/drop attacks—often provoked by ipsilateral arm exertion.
HeartCoronary-subclavian stealAngina/ACS or LV dysfunction with an ipsilateral internal mammary (LIMA/RIMA) graft and proximal subclavian disease.
AccessDialysis dysfunctionLow flow, access-related ischemia, or pressure surveillance problems with ipsilateral AV access. Distinguish inflow disease from distal steal.
2
Bedside → duplex → anatomy
test only as far as the decision needsCompareBoth-arm BP + pulsesAxillary/brachial/radial/ulnar pulses, supraclavicular bruit, temperature, capillary refill, digital tissue, neurologic and coronary symptoms.
LocalizeDuplex ultrasoundSubclavian velocities/waveforms plus vertebral flow direction. Reactive-hyperemia testing can unmask intermittent reversal.
ConfirmCTA or MRAUse when duplex is abnormal/equivocal or intervention is being planned. Image the aortic arch and supra-aortic anatomy.
Treat riskAtherosclerosis bundleAntiplatelet when indicated, statin, BP/diabetes control, tobacco treatment. Use the higher-pressure arm for systemic BP management unless bilateral disease.
3
Who needs revascularization?
symptoms and planned conduits matter| Setting | Recommendation | Route |
|---|---|---|
| Symptomatic disease | Revascularize for TIA/stroke from steal, coronary-subclavian steal, dialysis-access dysfunction, disabling arm ischemia, tissue loss, or impaired quality of life. | Endovascular angioplasty/stent is common first-line. Open transposition/bypass for occlusion, unsuitable anatomy, or failed endovascular therapy. |
| Selected asymptomatic | Consider before CABG using an ipsilateral internal mammary artery, with ipsilateral dialysis access, or significant bilateral disease that prevents reliable BP surveillance. | Multidisciplinary planning. No routine procedure for an incidental unilateral stenosis. |
| Steal phenomenon only | Retrograde vertebral flow without compatible symptoms usually receives medical therapy and observation. | Reassess if arm, posterior-circulation, coronary, or access symptoms develop. |
Emergency: sudden painful cold arm, absent Doppler signals, sensory/motor loss, digital threat, or suspected coronary steal with ACS → immediate vascular/cardiac evaluation. Do not delay a threatened arm for an outpatient imaging sequence.
VTE
Possible PEDyspnea, pleuritic chest pain, syncope, hypoxemia, tachycardia, or shock → use the pulmonary embolism emergency pathway.
PhlegmasiaMassive painful swelling + cyanosis, sensory/motor loss, venous gangrene, or shock → limb/life emergency.
First testUse a validated DVT pretest-probability rule. D-dimer rules out low/unlikely disease. It never rules DVT in.
ImageCompression duplex is the primary diagnostic test. Compare with prior imaging for suspected recurrent ipsilateral DVT.
1
Suspected DVT — probability directs testing
avoid indiscriminate D-dimerLow / unlikely PTPHigh-sensitivity D-dimerNegative excludes DVT. Positive requires proximal or whole-leg ultrasound.
Likely / high PTPUltrasound firstDo not use a D-dimer alone to exclude high-probability disease.
Negative proximal USRepeat in ~1 weekIf suspicion persists and no alternative diagnosis. A negative whole-leg study generally needs no repeat.
Positive studyName the segmentProximal = popliteal or above. Isolated distal = calf veins only. Extent and provoking factors guide treatment.
2
Confirmed DVT — treat clot and context
minimum treatment phase = 3 months| Clot / context | Action | Duration / guardrail |
|---|---|---|
| Proximal DVT | Full-dose anticoagulation unless contraindicated. | At least 3 months. Provoked by a resolved major transient factor usually stops after the treatment phase. |
| Isolated distal DVT | Anticoagulate if severe symptoms or extension risk (active cancer, prior VTE, unprovoked, inpatient/immobile, extensive/multivein, near popliteal). | If low risk, serial ultrasound weekly for 2 weeks. Anticoagulate if extension. |
| Unprovoked / persistent / recurrent | Consider extended or indefinite anticoagulation when recurrence benefit outweighs bleeding risk. | Reassess bleeding, renal/hepatic function, interactions, goals, and adherence periodically. |
| Do not do routinely | No thrombolysis for ordinary proximal DVT. No IVC filter when anticoagulation can be given. No surveillance ultrasound solely to decide duration. | Filter only for an absolute anticoagulation contraindication. Retrieve promptly once anticoagulation resumes. |
3
Common oral regimens
acute VTE doses are not AF dosesApixaban10 mg BID × 7 days → 5 mg BIDNo heparin lead-in. After ≥6 months, 2.5 mg BID is a labeled extended-prevention dose. Do not automatically apply the AF age/weight/creatinine rule to acute VTE.
Rivaroxaban15 mg BID with food × 21 days → 20 mg daily with foodNo heparin lead-in. After ≥6 months, 10 mg daily is a labeled extended-prevention dose.
Before prescribing: check CBC/platelets, creatinine/CrCl, hepatic function, pregnancy/breastfeeding, bleeding, weight/absorption, and drug interactions. Pregnancy, triple-positive antiphospholipid syndrome, severe renal/hepatic disease, active luminal GI/GU cancer, or strong P-gp/CYP3A interactions may favor LMWH/VKA or specialist guidance.
4
Superficial venous thrombosis (SVT)
whole-leg ultrasound · measure length + junction distanceMain saphenous SVT ≤3 cm from SFJFull-dose anticoagulationTreat for at least 6 weeks. Specialist review may support longer treatment in selected high-risk cases. Concomitant DVT follows the DVT pathway.
Above knee · ≥5 cm long · >3 cm from SFJAnticoagulate 45 daysFondaparinux 2.5 mg SC daily. Rivaroxaban 10 mg daily is a guideline-supported oral alternative. These SVT uses are not specifically FDA-labeled. Saphenopopliteal-junction disease requires anatomy-specific specialist review.
Small + low riskSymptom careWalking, elevation, local compresses, and NSAID if safe. Repeat evaluation for extension, recurrence, axial/multifocal clot, cancer, or worsening symptoms.
PHLEGMASIA
Immediate vascular/interventional consultation + therapeutic heparin (often UFH), elevation, resuscitation, and urgent thrombus-removal planning. Imaging may define extent but must not delay treatment of a threatened limb.
Chronic venous disease is a pressure, reflux or obstruction syndrome. Not every swollen leg has venous disease. Typical symptoms worsen with standing and improve with elevation. Acute unilateral swelling still requires a DVT pathway. Whole-limb edema or venous claudication after iliofemoral DVT raises concern for central outflow obstruction.
1
Recognize, classify, and image
standing exam · CEAP · duplexPatternVenous cluesHeaviness/ache, dependent edema, varicosities, pruritus, hemosiderin, stasis dermatitis, lipodermatosclerosis, or a shallow irregular medial gaiter ulcer.
ClassifyCEAP clinical classC0 none · C1 telangiectasia · C2 varicose · C3 edema · C4 skin change · C5 healed ulcer · C6 active ulcer.
Primary testFull venous duplexEvaluate superficial/deep reflux, prior thrombosis, and obstruction while standing when feasible. Severe unilateral disease, collaterals, or venous claudication may need iliac/central imaging.
2
Compression — confirm arterial safety first
ABI + toe pressure when needed| Perfusion / setting | Compression plan | Guardrail |
|---|---|---|
| Adequate arterial supply | For active venous ulcer, multilayer/inelastic or adjustable compression targeting ≥40 mmHg at the ankle. Symptomatic edema often uses below-knee 20–40 mmHg. | Fit correctly. Pair with walking/calf-pump exercise and elevation. |
| Mixed arterial–venous | Modified compression <40 mmHg only under close supervision when ABI >0.6, ankle pressure >60, and toe pressure >30 mmHg. | Use toe pressure/TBI when ABI is unreliable or noncompressible. |
| Severe ischemia | No sustained compression if ABI <0.6, ankle pressure <60, or toe pressure <30 mmHg. | Stop and reassess for severe pain, neurologic change, tissue deterioration, or decompensated HF. |
3
Venous ulcer bundle
compression + wound + refluxWoundClean · debride · protectMoist absorbent dressing, periulcer skin care, nutrition and mobility. Measure serially.
InfectionTreat clinical infectionColonization is expected. Antibiotics only for spreading erythema/swelling, warmth, increasing pain, purulence, systemic signs, or deeper infection.
RefluxAblate early when suitableEarly endovenous treatment of superficial reflux plus compression accelerates active-ulcer healing. Treating reflux reduces recurrence.
After healingPrevent recurrenceContinue long-term compression, calf-pump activity, weight/skin care, and venous follow-up.
4
When to intervene or escalate
symptoms · anatomy · healing trajectoryReflux / obstruction
- Symptomatic axial GSV/SSV reflux favor endovenous intervention over indefinite compression when the patient is a candidate. No mandatory 3-month compression trial is medically required.
- Suspected iliac obstruction severe unilateral edema, venous claudication, collaterals, recurrent ulcer, or post-thrombotic disease → specialist imaging and possible stenting.
Do not miss
- Nonhealing / atypical ulcer reassess after 4–6 weeks for arterial disease, infection, malignancy, inflammatory ulcer, pressure, or central obstruction.
- Bleeding varicosity lie down, elevate, apply firm direct pressure/compressive dressing. Emergency care if ongoing, then prompt definitive venous treatment.
BOTTOM LINE
Compression is treatment only after arterial adequacy is considered. Classify with CEAP, map reflux/obstruction with duplex, combine compression with wound and calf-pump care, and treat correctable superficial reflux early in an active venous ulcer.
Renal artery stenosis does not establish renovascular causality. Decide whether the lesion plausibly explains hypertension, loss of renal function, or recurrent circulatory congestion. An incidental narrowing in a patient with stable BP and kidney function is a different problem from rapidly progressive disease.
1
One artery, two downstream questions
pressure and recoverable functionRenal artery narrowingReduced perfusion pressure can affect both pressure regulation and kidney tissue.
Pressure pathwayRenin activation → vasoconstriction and sodium retention.
Hypertension and congestion: assess clinical attribution.
Tissue pathwayIschemic tissue injury → microvascular loss and fibrosis.
A patent artery cannot guarantee recovery of a damaged kidney.
2
Clinical clues that justify targeted assessment
confirm the trajectory| Clue | What to establish before attributing it to stenosis |
|---|---|
| Resistant or rapidly worsening hypertension | Correct measurement, out-of-office BP, adherence, medication adequacy, and other secondary causes. Apparent resistance is not automatically renovascular hypertension. |
| Recurrent flash pulmonary edema / HF | Timing, BP surges, volume status, LV/valve disease, and ischemia. Look for bilateral disease or a solitary functioning kidney. |
| Unexplained kidney-function decline | Serial creatinine/eGFR, urine protein, kidney size, obstruction, nephrotoxins, and other renal disease. |
| Creatinine rise with ACE inhibitor / ARB | Recheck volume depletion, hypotension, NSAIDs, and bilateral/solitary-kidney disease. The response is a clue, not proof. |
| Early-onset hypertension or known FMD | Consider renal FMD even without the typical atherosclerotic risk profile. |
3
Use each test for its own question
do not intervene on a velocity aloneDuplexFlow + kidney sizeUsual first test for suspected atherosclerotic stenosis. Interpret velocities and renal-aortic ratios with validated laboratory criteria.
CTA / MRADefine the arterial treeClarify equivocal duplex or plan intervention. Choose for renal function, contrast considerations, and local image quality.
ParenchymaIs recovery plausible?Kidney size/cortex, proteinuria, and the eGFR trajectory inform viability. A resistive index describes downstream resistance, not stenosis severity.
AngiographyResolve a treatment decisionReserve invasive anatomy and pressure assessment for selected cases when it can change management.
Pattern recognition: ostial/proximal plaque suggests atherosclerosis. Mid-distal beading suggests multifocal FMD. Distribution guides the differential, but image artifacts, dissection, and inflammatory arterial disease remain alternatives. Continue to treatment decisions or FMD assessment.
Routine stenting does not improve outcomes in the average stable atherosclerotic RAS population. The useful next question is whether this patient has a high-risk presentation, a hemodynamically important lesion, and a kidney or clinical syndrome that may still respond.
1
CORAL: what the randomized result establishes
947 participants · medical therapy in both armsPopulationAtherosclerotic RASHypertension on ≥2 agents or CKD. Randomized to medical therapy with or without a renal artery stent.
CV / renal composite35.1% vs 35.8%Stent versus medical therapy. HR 0.94 (95% CI 0.76–1.17), P=.58. Median follow-up 43 months.
Systolic BPOnly 2.3 mmHg lowerA modest mean BP difference favored stenting, without a significant clinical-event benefit.
Read the inclusion boundary: recent HF admission was excluded from major renal-stenting trials. That limits extrapolation to flash pulmonary edema. It does not prove that intervention benefits every patient excluded from a trial.
2
Medical management is active treatment
BP · vascular risk · kidney surveillance| Target | Practical approach |
|---|---|
| Blood pressure | Use a tolerated regimen and home/ambulatory readings. ACE inhibitors/ARBs may be effective. Monitor creatinine and potassium, particularly with bilateral severe disease or a solitary kidney. |
| Atherosclerotic risk | Statin-based lipid lowering, appropriate antiplatelet therapy, tobacco treatment, and diabetes care. Reconcile bleeding risk and other anticoagulation indications. |
| Renal trajectory | Follow eGFR, potassium, urine protein, BP burden, and congestion. Worsening despite a well-delivered plan should trigger reassessment rather than serial drug escalation alone. |
3
Refer selectively when the syndrome changes the stakes
multidisciplinary renal / vascular reviewCongestionRecurrent flash edemaA strong clinical signal when severe RAS is plausibly causal. Assess other cardiac causes and the distribution of renal disease.
KidneyRapid loss of functionEspecially bilateral severe disease or stenosis to a solitary functioning kidney. Weigh viability and alternative kidney diagnoses.
PressureProgressive / refractory BPVerify true resistance and significant anatomy. Recent deterioration may be more informative than years of stable hypertension.
4
Observational signals support selection, not certainty
separate referral from a promiseIn a prospective two-center high-risk cohort, 14 of 17 successfully treated patients with recurrent HF or sudden pulmonary edema had no further HF admission during follow-up. This was an uncontrolled selected cohort: improvement cannot be assumed for every patient with RAS, and procedural success, selection, and concurrent treatment affect interpretation.
Before a procedure: document the target outcome (BP, congestion, renal preservation), expected benefit, kidney viability, contrast/embolization/access risks, and a follow-up plan. Technical opening of the artery is not the clinical endpoint.
Fibromuscular dysplasia (FMD) is a disorder of the wall of medium-sized arteries. Abnormal wall structure can narrow the artery or coexist with dilation, aneurysm, and dissection. It is nonatherosclerotic and noninflammatory. Renal and neck arteries are common sites. Most diagnosed patients are women, but men and other age groups can be affected. Compare the arterial patterns.
1
Read the morphology and the distribution
stenotic lesions establish the diagnosis| Pattern | Meaning | Guardrail |
|---|---|---|
| Multifocal FMD | Alternating arterial narrowings and dilatations, commonly in mid-distal renal or cervical arteries. | Do not confuse beading with catheter spasm, motion artifact, or another arteriopathy. |
| Focal FMD | A discrete focal or tubular stenosis. Not all FMD has the classic beaded appearance. | Exclude atherosclerosis, dissection, and inflammatory disease using the full clinical and imaging context. |
| Aneurysm / dissection / tortuosity alone | May coexist with FMD and require their own evaluation. | These findings alone do not establish FMD without a focal or multifocal FMD lesion. |
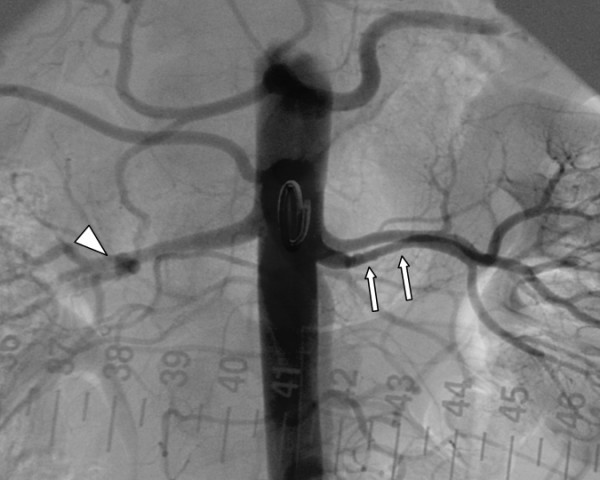
2
Start at the presenting vascular bed
then look beyond itRenalHypertension / asymmetryEarly, accelerated, or resistant hypertension, a bruit, or kidney asymmetry are clues. CTA is usually the initial test for suspected renal FMD. Contrast-enhanced MRA is an alternative. Duplex requires specific FMD expertise.
Cervical / intracranialTinnitus / headache / ischemiaPulsatile tinnitus and headache can be clues, but are nonspecific. CTA/MRA evaluates the neck and intracranial circulation. New neck pain with neurologic or retinal symptoms requires urgent assessment.
CoronarySCAD connectionSCAD can be a clue to extracoronary arteriopathy. FMD and SCAD are associated diagnoses, not interchangeable labels.
3
Why the initial diagnosis triggers broader imaging
registry contextAmong 921 referred U.S. FMD Registry patients, 200 (21.7%) had aneurysm and 237 (25.7%) had dissection. Overall, 384 (41.7%) had either by diagnosis. These are clinical-registry findings, not population screening prevalence.
Once the qualifying lesion is confirmed: record the affected arteries and obtain brain-to-pelvis CTA or contrast-enhanced MRA, including intracranial arteries. Give each aneurysm or dissection its own size, location, symptoms and care plan. Initial mapping does not prescribe repeated whole-body scans. See individual surveillance.
Clinical distinction: do not treat FMD with immunosuppression merely because an artery is irregular. If systemic inflammation, vessel-wall inflammation, or a vasculitic phenotype is present, reopen the diagnosis with the appropriate specialists.
A stable FMD diagnosis is the start of a longitudinal plan. Organize care around BP control, symptoms, renal function, and any aneurysm or dissection. A procedure is reserved for a specific clinical problem. The imaging label alone is not an indication.
1
Three different reasons to prescribe medication
avoid importing the entire PAD regimen| Clinical target | Approach | Evidence boundary |
|---|---|---|
| Renovascular hypertension | ACE inhibitor or ARB often fits the mechanism. Check kidney function and potassium after initiation or escalation. Additional agents follow the BP phenotype. | Extra caution with bilateral severe renal disease, a solitary kidney, or volume depletion. |
| Thromboembolic prevention | Aspirin 75–100 mg daily may be reasonable after considering prior ischemia, dissection, revascularization, and bleeding risk. | Consensus-based. A 2024 evidence review found no demonstrated FMD-specific benefit to justify automatic lifelong aspirin for every asymptomatic patient. Record the indication and bleeding assessment. |
| Lipids / atherosclerosis | Use a statin when ordinary lipid or ASCVD indications are present. | FMD by itself is not an established statin indication or a proven statin-responsive lesion. |
2
Renal FMD: when angioplasty enters the plan
benefit depends on the syndromeClinical needAttribute the hypertensionAssess severity, duration, medication burden, and kidney function. Confirm that a renal FMD lesion is plausibly causal.
Specialist assessmentAnatomy + hemodynamicsA striking beaded artery is not necessarily a significant pressure obstruction. Expert catheter assessment can resolve selected treatment decisions.
RevascularizationBalloon angioplastyUsually the preferred renal FMD technique. Routine stenting is avoided. Reserve stents mainly for complications such as flow-limiting dissection.
Clinical responseReassess medicationsTrack BP and renal function promptly after treatment. Improved anatomy does not guarantee cure of long-standing hypertension.
3
Build a follow-up plan that names the findings
at least annual clinical reviewAt reviewBP · kidney function · symptomsReview home BP, medication tolerance, renal function in renal FMD, new neurologic or vascular symptoms, and tobacco exposure. Address headache or tinnitus rather than assuming every symptom requires intervention.
ImagingTailor to the arterial lesionAn aneurysm, dissection, or treated renal lesion has a different surveillance question from uncomplicated stable FMD. There is no single evidence-based whole-body imaging interval for everyone.
4
Prepare for the events that change urgency
clear symptom instructionsNeurologicNew focal symptomsSudden weakness, speech difficulty, monocular visual loss, or a thunderclap headache needs emergency evaluation.
Arterial painNew severe pain / ischemiaAcute chest, abdominal, flank, or limb symptoms need assessment for dissection, aneurysm complications, or ischemia.
Planned life eventsPregnancy / major proceduresReview BP drugs, known aneurysms, and prior dissections with specialists in advance. See follow-up, activity and family counseling.
The medical comparator has changed. Contemporary randomized evidence helps calibrate a narrow preventive margin in asymptomatic disease. It does not replace the urgent evaluation of a recent ipsilateral retinal or hemispheric event. That pathway remains in chapter 5.
1
CREST-2: two parallel randomized trials
asymptomatic stenosis ≥70%| Randomized comparison | 4-year primary outcome | Interpretation |
|---|---|---|
| Transfemoral stenting + intensive medical management versus intensive medical management n=1,245 | 2.8% vs 6.0% Absolute difference 3.2 percentage points. P=.02 | Benefit for the prespecified composite in the trial setting, with an early procedural hazard. |
| CEA + intensive medical management versus intensive medical management n=1,240 | 3.7% vs 5.3% P=.24 | No statistically significant benefit for the primary outcome. This does not establish equivalence. |
Endpoint: stroke or death through day 44, then ipsilateral ischemic stroke through four years. Early events occurred with procedures: stenting had seven strokes and one death versus none with medical therapy. CEA had nine strokes versus three with medical therapy.
Do not compare across randomizationsCAS superiority to CEA was not testedSeparate controls and separate trials cannot produce a direct randomized ranking of the two procedures.
Do not transfer device evidenceTransfemoral CAS is not TCARThe stenting result does not directly establish the same benefit for a different access/protection strategy.
2
ECST-2: a different risk-selected population
two-year interim analysis429 patients with asymptomatic or low/intermediate-risk symptomatic stenosis ≥50% and predicted five-year ipsilateral stroke risk <20% were assigned to optimized medical therapy with or without revascularization. The hierarchical endpoint included fatal events, nonfatal stroke, nonfatal MI, and new silent cerebral infarction. The win ratio was 1.01 (95% CI 0.60–1.70), P=.97. Neither strategy was favored at two years.
Interpret the boundary: a smaller, risk-selected interim trial does not cancel established treatment of recently symptomatic high-risk disease. Its population, follow-up, and endpoint differ from CREST-2. Identical slogans would conceal clinically important differences.
3
Make the asymptomatic consultation concrete
record the expected net benefit| Decision question | What belongs in the discussion |
|---|---|
| Is the patient actually asymptomatic? | Review laterality and timing of retinal/cerebral events, competing AF/cardioembolism, and brain imaging. |
| Is medical therapy delivered? | Adherence, antiplatelet plan, lipid lowering, BP control, tobacco exposure, and risk-factor follow-up. |
| Can a small delayed benefit exceed early risk? | Life expectancy, functional status, anatomy, patient preferences, and audited local stroke/death risk. |
| What will trigger reassessment? | New ipsilateral symptoms require urgent review. Progression or concerning plaque findings warrant a renewed individualized discussion. |
An angiogram shows a lumen. A pressure index does not measure tissue oxygenation. Choose the test for the unresolved question: is disease present, where is the hemodynamic obstruction, or is local perfusion sufficient to support healing?
1
Follow the signal from the arterial tree to the wound
complementary measurements1. Anatomic routeDuplex · CTA · MRA
Where is the lesion?
2. Hemodynamic effectABI · TBI · waveforms
What reaches the limb?
3. Local healing conditionsToe pressure · TcPO₂ · SPP
Interpret beside the wound.
A technically successful procedure still requires a clinical and tissue-perfusion response.
2
Choose the next test by the discordance
resting ABI categories: chapter 1| Clinical situation | Test | What it adds |
|---|---|---|
| Exertional symptoms. ABI normal / borderline | Exercise treadmill ABI | Challenges flow reserve. A normal resting pressure does not exclude an exertional limitation. |
| ABI >1.40 | TBI with toe waveforms | Assesses less frequently noncompressible digital arteries. TBI ≤0.70 is abnormal. |
| Need lesion-level localization | Segmental pressures, PVR, Doppler waveforms | Locate hemodynamic deterioration. Duplex adds a lesion-level anatomic and velocity assessment. |
| Rest pain / wound / gangrene | Toe pressure and/or TcPO₂ / SPP | Address local perfusion even when ankle pressure looks acceptable. Add anatomy when planning revascularization. |
3
Thresholds support decisions. Context determines them
warm room · reproducible techniqueAbsolute toe pressure<30 mmHgSevere ischemia. Associated with greater amputation risk and a lower likelihood of wound healing.
Transcutaneous oxygenTcPO₂ >30 mmHgSupports healing potential. Interpret with local tissue conditions and the clinical examination.
Skin perfusion pressureSPP >40 mmHgSupports healing potential. It is not a promise that the wound will close.
4
When the measurements disagree
check the assumption before repeating the labelHigh ABI with a threatened footThink noncompressibilityDiabetes/CKD may make cuff pressure falsely reassuring. Obtain digital or tissue measurements instead of concluding that arterial supply is normal.
Adequate perfusion with a persistent ulcerReopen the wound differentialEvaluate neuropathic pressure, venous disease, infection, edema, inflammation, and nutrition. More arterial intervention is not the automatic answer.
Do not delay emergency care: abrupt coolness, new sensory loss, or weakness belongs in the acute limb ischemia pathway. Outpatient physiologic testing is not the first step for an immediately threatened limb.
The clinical endpoint is a healed, functional limb with an acceptable treatment burden. Patency matters, but so do wound closure, infection control, pain, walking, survival, and the patient's goals. Use the acute CLTI bundle in chapter 3 and document which outcome the proposed intervention should improve.
1
Wound, ischemia, infection: keep all three visible
WIfI is a staging system, not a wound photographWoundExtent + functional consequenceRecord location, depth, exposed structures, tissue loss, and serial measurements. Offloading is part of treatment.
IschemiaObjective perfusionUse the most reliable limb measurements. Do not let a calcified ABI conceal poor toe or tissue perfusion.
Foot infectionDepth + systemic responseCoordinate antibiotics and drainage/debridement with perfusion restoration. Re-stage after major clinical changes.
2
Revascularization evidence depends on the enrolled anatomy
conduit · operative risk · target vessels| Trial | Result to retain | Clinical limitation |
|---|---|---|
| BEST-CLI CLTI with infrainguinal disease | With an adequate single-segment great saphenous vein, surgery reduced major adverse limb events or death: 42.6% vs 57.4%. HR 0.68 (95% CI 0.59–0.79). Without that conduit, no significant difference was shown. | The first-cohort result should not be applied to a patient without suitable vein or without acceptable surgical risk. Major repeat limb interventions contributed to the endpoint. |
| BASIL-2 CLTI requiring infrapopliteal revascularization | Vein-bypass-first produced more major amputation or death than endovascular-first: 63% vs 53%. Adjusted HR 1.35 (95% CI 1.02–1.80), driven mainly by mortality. | A below-knee population and a different primary endpoint. “Bypass always wins” and “endovascular always wins” both lose the patient-selection question. |
Shared decision: ask whether the patient has usable vein, an appropriate target, sufficient life expectancy and function to benefit, acceptable perioperative risk, and a plan for repeat intervention if needed. The trials compare strategies in enrolled patients, not procedures in the abstract.
3
After revascularization, track a clinical response
symptoms override the routine calendar| Finding / procedure | Follow-up action |
|---|---|
| New limb signs or symptoms | Clinical reassessment plus ABI and arterial duplex. Sudden ischemic features require emergency evaluation. |
| Stable autogenous infrainguinal vein bypass | ABI/duplex at 1–3 months, 6 months, 12 months, then annually is reasonable. |
| Stable endovascular procedure | The same 1–3, 6, and 12-month then annual ABI/duplex schedule is reasonable. Tailor to the intervention and local vascular plan. |
| Prosthetic infrainguinal bypass | The effectiveness of routine ABI/duplex surveillance in an asymptomatic patient is uncertain. Follow the operating team's individualized plan. |
4
If the wound is not improving, identify the missing condition
do not equate patency with healingArteryRestenosis / residual disease?Compare the clinical exam and objective perfusion with baseline.
TissueInfection / edema?Reassess depth, drainage, inflammatory change, and local oxygenation.
MechanicsPressure still present?Check footwear, offloading, walking mechanics, and caregiver feasibility.
PatientNutrition / function / goals?Revisit the whole plan with wound, vascular, and rehabilitation teams.
FMD belongs in vascular medicine. It is an arterial-wall disorder, whereas vasculitis is inflammation of the vessel wall and atherosclerosis is plaque disease. Each can cause stenosis or aneurysm, so an abnormal angiogram alone cannot select the treatment.
1
What does FMD look like?
lumen silhouettes · not tissue sectionsNormal lumen
Smooth contour with a relatively even caliber.
Focal FMD
One short or tubular stenosis. Beading is not required.
Multifocal FMD
Alternating narrowing and dilation: the classic string of beads.
2
Compare the whole clinical pattern
distributions overlap| Process | Clues | Clinical implication |
|---|---|---|
| Atherosclerosis | Plaque, sometimes calcified, with conventional ASCVD risk. Renal disease often involves the ostium/proximal artery. | Manage atherosclerotic risk and the ischemic syndrome. A stenosis alone does not mandate intervention. |
| FMD | Focal stenosis or mid-distal multifocal beading, often renal or cervical. May coexist with aneurysm, dissection or tortuosity. | Confirm a qualifying lesion, map other arterial beds, and treat BP or specific complications. No immunosuppression for FMD itself. |
| Vasculitis | Vessel-wall inflammation and a compatible systemic or organ pattern. Wall thickening, edema or enhancement can support selected diagnoses. | Establish the named disease and activity. Normal inflammatory markers alone do not exclude vasculitis. Use the vasculitis pathway. |
3
Know when to reopen the differential
one image is not the diagnosisAneurysm or dissection without an FMD lesionConsider isolated dissection, a heritable arteriopathy, or other causes. Visceral arterial injury can also reflect segmental arterial mediolysis, another noninflammatory process.
A beaded appearance that does not fitReview source images with vascular imaging expertise. Spasm, standing waves, motion and other artifacts can mimic FMD.
Next step: suspected FMD → diagnosis and screening → treatment → longitudinal care. New organ ischemia requires urgent care while the cause is clarified.
Give the patient a concise arterial history. Record confirmed FMD sites, baseline brain-to-pelvis imaging, aneurysm measurements, previous dissections and interventions, medications, and the clinician responsible for surveillance. Plan at least annual clinical review, with earlier assessment for new symptoms.
1
Screening and surveillance answer different questions
avoid automatic annual whole-body CTA| Finding | Follow-up question |
|---|---|
| Stable FMD | Review symptoms, home BP, medications and renal function when renal arteries are involved. Repeat imaging depends on the lesion and clinical change. No universal interval is established. |
| Intracranial aneurysm | Specialist assessment of size, location, shape, growth and patient risk determines observation versus treatment. In 669 imaged women in the U.S. registry, 86 (12.9%) had an intracranial aneurysm. This is a selected registry estimate, not an annual rupture risk. |
| Cervical artery dissection | Use a stroke/neurovascular pathway. Individualize antithrombotic choice, generally for 3–6 months, and follow-up imaging. This is a separate indication from aspirin considered for uncomplicated FMD. |
| After renal angioplasty | Check BP response, drug requirements and renal function. Arrange duplex surveillance with the treating team and investigate recurrent hypertension or declining renal function. |
2
Activity, headache and neck symptoms
individual counselingRemain active with a tailored planEncourage moderate aerobic activity. Discuss heavy straining, breath-holding, contact injury and extreme neck movement, especially after dissection or with aneurysms. Avoid high-velocity cervical manipulation. Evidence is largely expert guidance, not exercise trials.
Do not dismiss a new pain patternManage stable migraine and tinnitus, but sudden severe headache, new head/neck pain with Horner syndrome, or focal neurologic symptoms warrants urgent assessment. Review vasoconstricting migraine drugs carefully after SCAD or cervical dissection.
3
Pregnancy and family questions
plan before conceptionPregnancy is an individualized decisionReview BP control, kidney function, aneurysms and previous dissections with maternal-fetal medicine and vascular specialists. Replace ACE inhibitors/ARBs before pregnancy. Registry evidence supports attention to gestational hypertension and preterm birth, not a blanket prohibition on pregnancy.
FMD has no routine diagnostic gene testRoutine genetic testing or vascular imaging of asymptomatic relatives is not recommended solely for FMD. Syndromic features or a strong family history of aneurysm, dissection or unexplained sudden death may justify evaluation for a different heritable arteriopathy.
Emergency symptoms: stroke or retinal symptoms, thunderclap headache, or acute severe chest, abdominal, flank or limb pain need urgent assessment. A prior FMD diagnosis should inform that evaluation without determining the cause in advance.
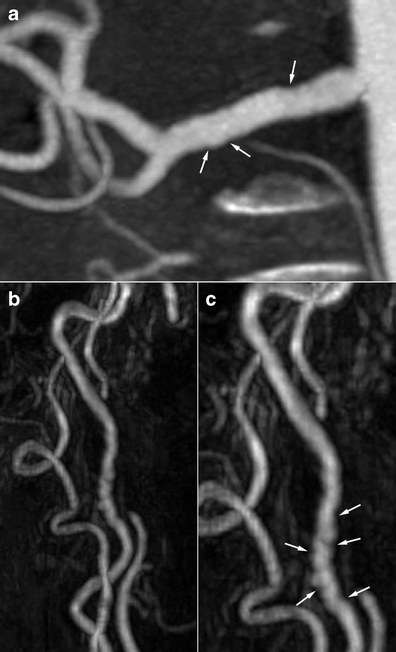
Find the alternating narrow and dilated segments. These published examples show multifocal FMD in renal and cervical arteries. Read the original panel letters and arrows alongside the captions.
1 · Renal and carotid involvement
2 · Compare the imaging modalities
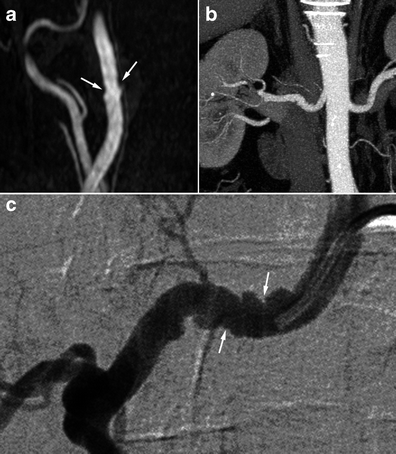
Pattern is not physiology. These examples do not determine a pressure gradient or an indication for angioplasty. Focal FMD can lack beading. Aneurysm, dissection or tortuosity alone does not establish FMD, and imaging morphology does not prove a histologic subtype.
Use the images with the clinical pathway: diagnosis and screening · management · arterial patterns and mimics · follow-up.